For clinicians and neighbourhood partners

Published rules.
No language model.
A person holds every decision.

Four diagrams and a working tool. Between them they answer the questions a clinical team, an information governance lead and a commissioner each ask first — and they answer them differently, which is why there are four.

EngineDeterministic rules, version-controlled
InferenceNone at any stage below stage 3
Register31 rules, each with a named owner
StatusConcept in development
Diagram one

One request, one thread,
one record of what happened

Twelve steps from a person noticing a change to the data that proves the model works or stops it. The lanes matter more than the boxes: everything in the top two lanes is gathering, routing and chasing. The amber steps in the bottom lane are clinician-only and stay that way.
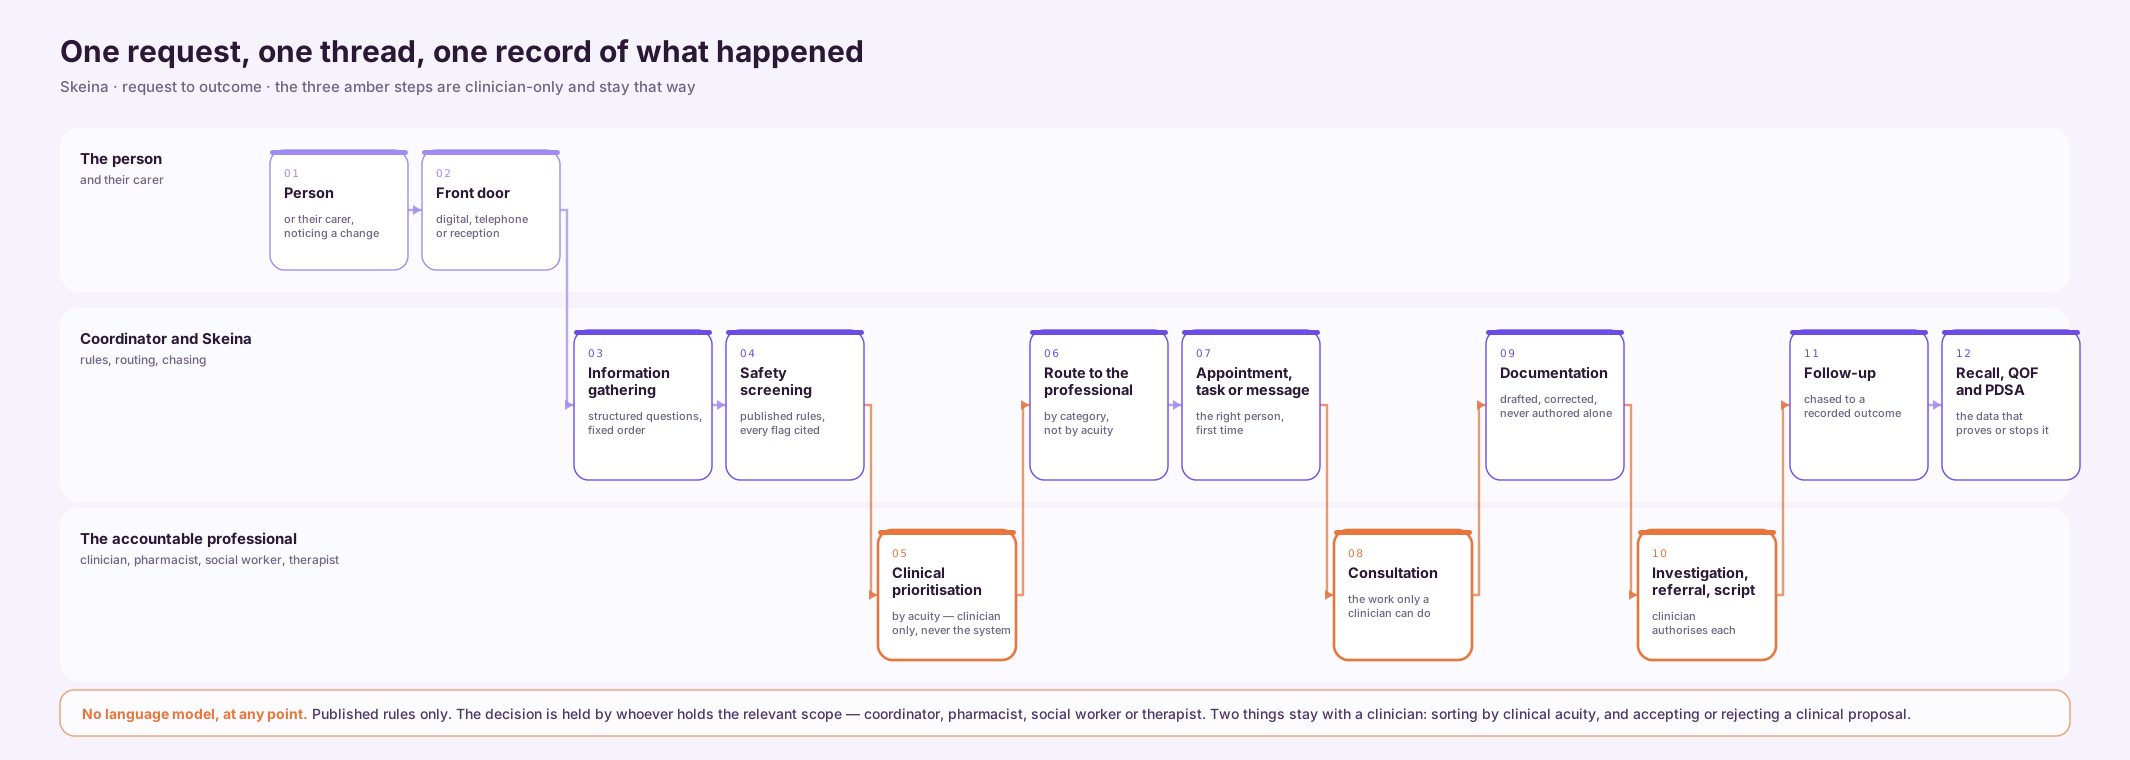
Swimlane diagram of the twelve steps from person to recall data, showing which steps belong to the person, to the coordinator and Skeina, and to the accountable professional
Fig 1Request to outcome Open full size ↗

Scroll the diagram sideways

The step people look for

Step 05, clinical prioritisation, sits in the professional's lane rather than the system's. Clinical acuity assessment and acceptance of clinical proposals remain with appropriately qualified professionals; Skeina does not autonomously make or execute clinical decisions. Whether any Skeina function qualifies as software as a medical device will nevertheless be determined from its intended purpose and functionality, with formal MHRA advice sought before deployment. We have deliberately designed Skeina to minimise autonomous clinical decision-making and maximise inspectability — that is a safety architecture, not a claimed regulatory exemption.

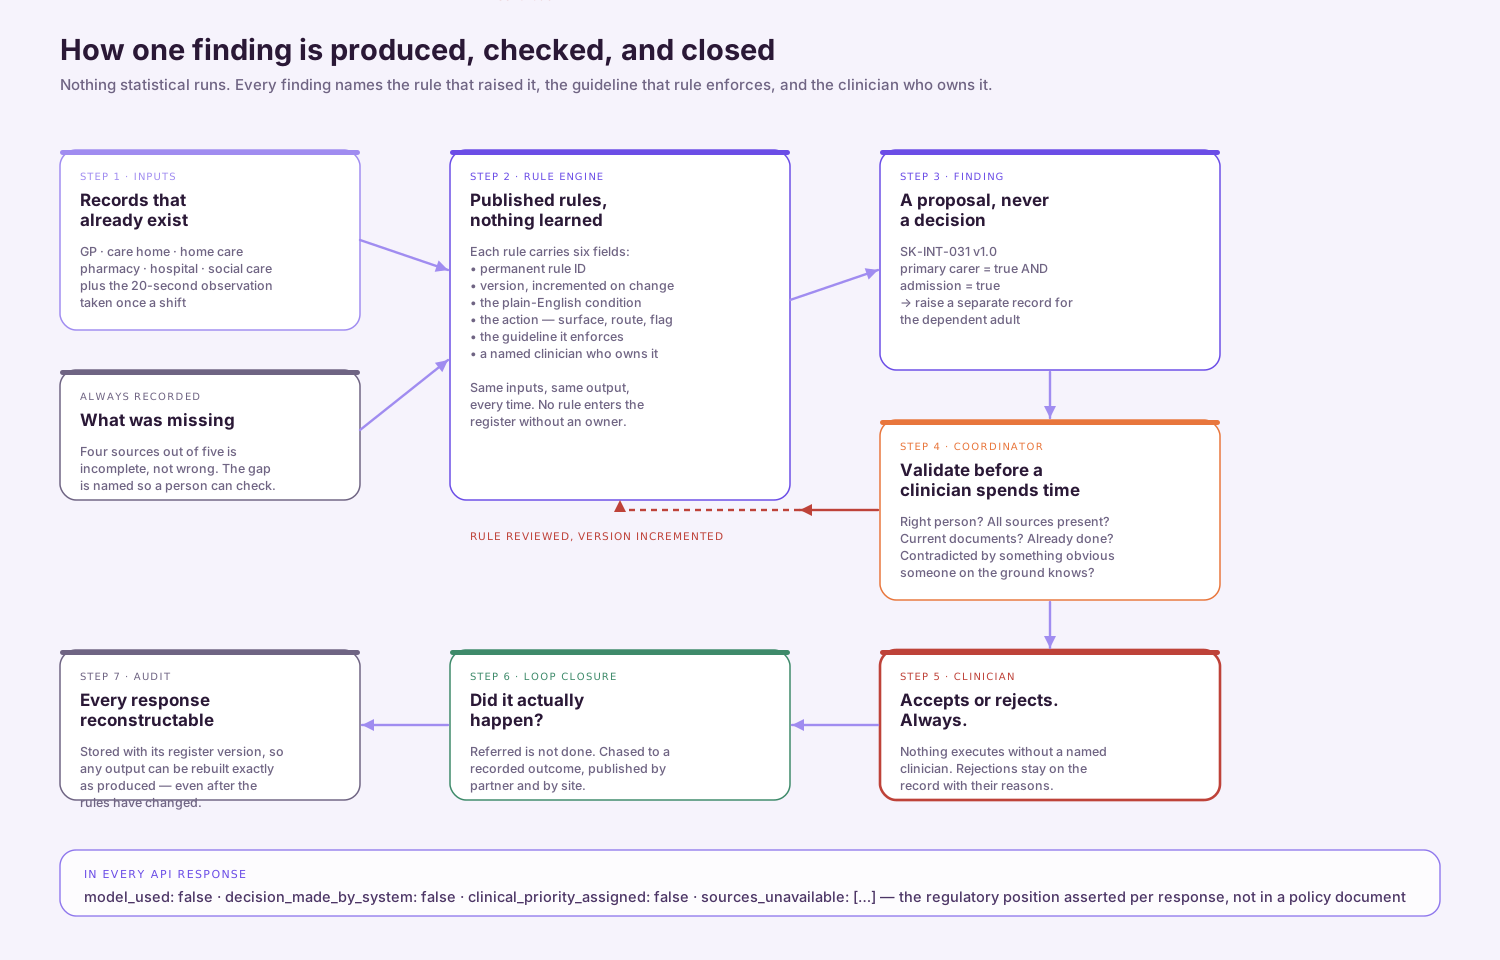
Diagram two

The system holds the information.
A person holds the decision.

And one decision right sits above the professional lanes: the person. The person decides whether they want non-mandatory help, what outcome matters, whether a proposed community referral is acceptable, and whether the outcome counts as success. Declining help is a recorded, respected outcome — the platform must never become an elegant system in which professionals remain the only decision-makers.

Decision rights follow professional scope, not seniority. A pharmacist decides a medicines question within their competence. A social worker decides a Care Act matter. A coordinator decides routing. Every rule in the register names which of them holds its decision.

Five columns showing what the care coordinator, pharmacist, clinician, social worker and therapy services each decide, with the constraint on each
Fig 2Decision rights by scope Open full size ↗

Scroll the diagram sideways

Two decisions that never move

Sorting by clinical acuity, and accepting or rejecting a clinical proposal. Both stay with a clinician. Not because other professions are less capable — because these are the two points where clinical accountability sits, and no colleague would want them arriving by default.

The question a CQC inspector will ask

Who is accountable when a coordinator routes something that turns out to be clinical? The answer is built into the escalation list rather than left to judgement: over-escalating carries no penalty and must never be discouraged, formally or informally. A falling escalation rate is investigated rather than celebrated, because it usually means someone has learned to predict what the clinician will say.

Diagram three

How one finding is produced,
checked, and closed

This is the information governance diagram. It follows a single finding from the records that already exist, through the rule that raised it, past the coordinator who validates it and the clinician who accepts or rejects it, to the outcome and the audit trail.

Seven-step diagram showing inputs, rule engine, finding, coordinator validation, clinician decision, loop closure and audit, with a send-back loop returning to the rule register
Fig 3The rule engine and its safety loop Open full size ↗

Scroll the diagram sideways

Follow the red line. When a coordinator sends a finding back, the reason is recorded and the rule is reviewed — and if it changes, the version increments and the old one is retained. Send-backs are the primary quality signal in the early stages. A send-back rate falling to zero is a warning, not a success.

6

Mandatory fields on every rule, including a named clinician who owns it

0

Findings that execute without a person accepting them

31

Rules currently in the register, all readable in one sitting

1

Version token stored with every response, so any output can be rebuilt exactly

What every API response asserts

model_used: false · language_model_used: false · logic: "deterministic_conditional_rules" · statistical_inference: false · decision_made_by_system: false · clinical_priority_assigned: false · sources_unavailable: […]

The regulatory position stated per response, machine-readable, rather than described in a policy document. Worth writing into any integration contract.

Diagram four

Earning the right to automate,
one gate at a time

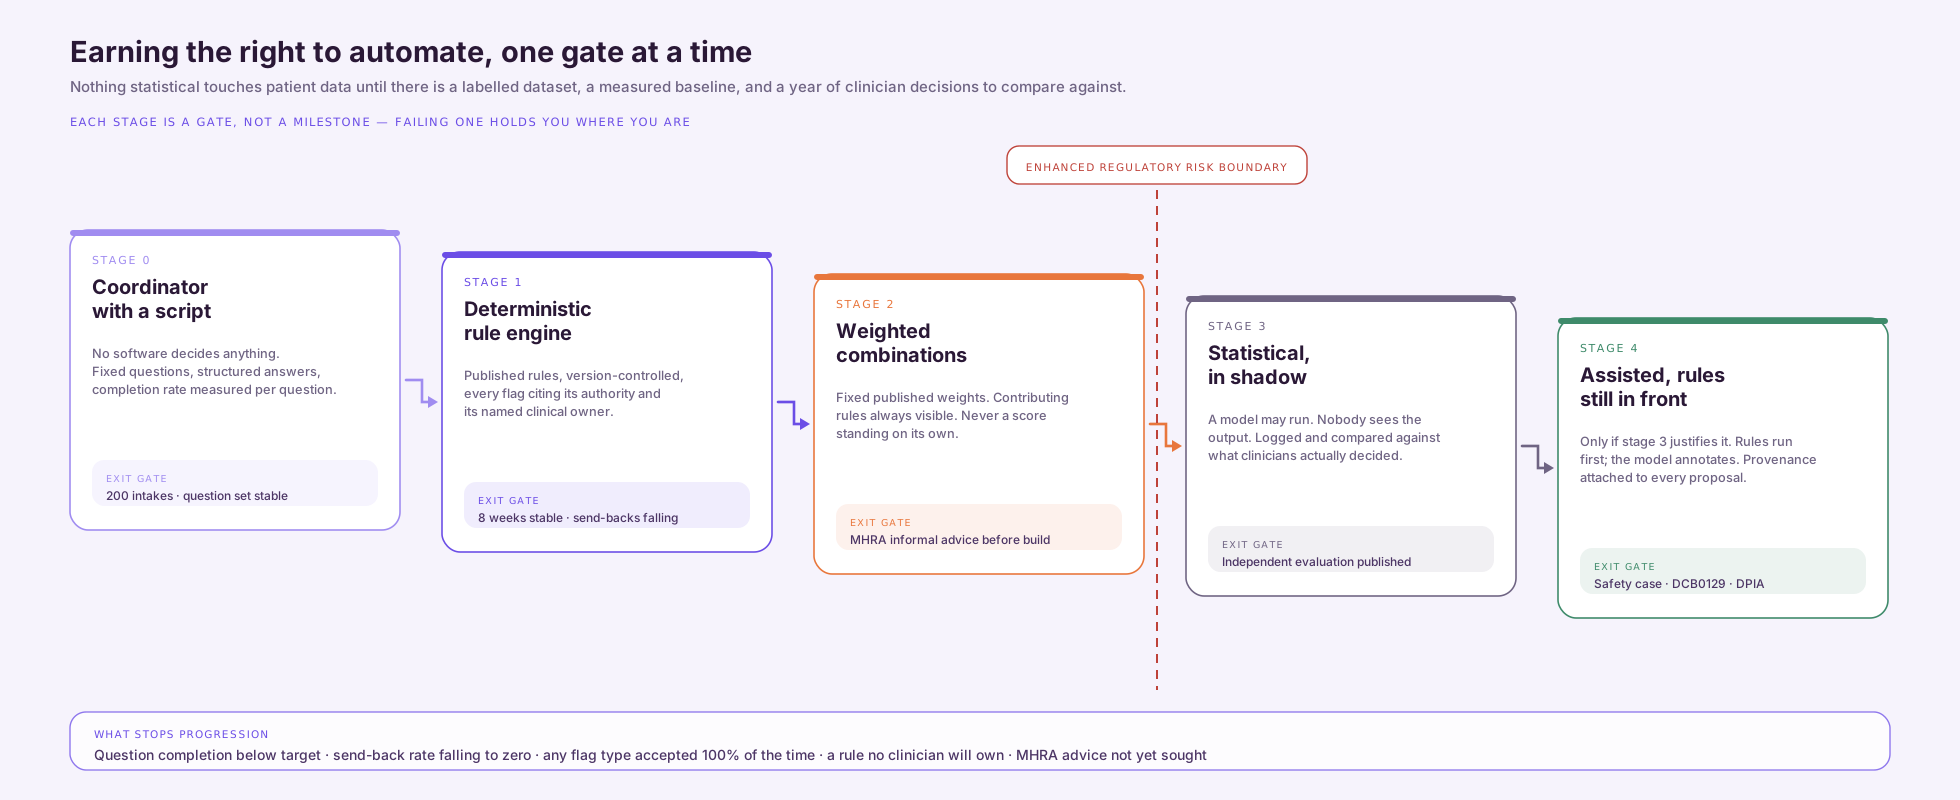
The question a commissioner actually wants answered is when the AI arrives. The answer is: not until four gates have been passed, and here is exactly what stops it at each one. Nothing statistical touches patient data until there is a labelled dataset, a measured baseline, and a year of clinician decisions to compare against.

Five stages rising left to right from coordinator with a script to assisted, each with an exit gate, and a dashed line marking an enhanced regulatory risk boundary at stage 3
Fig 4Stage 0 to stage 4, with gates Open full size ↗

Scroll the diagram sideways

The dashed red line after stage 2 marks an enhanced regulatory risk boundary, not the start of regulation. Formal medical-device qualification applies throughout development and is reassessed whenever intended purpose or functionality changes; a deterministic rule can still perform a medical purpose. Stage 3 introduces additional classification and validation considerations — it is not the first point at which medical-device regulation may apply. Informal MHRA advice belongs early, and before that boundary in any event.

What stops progression

  • Question completion below target — the intake is wrong and everything downstream inherits it
  • Coordinator send-back rate falling to zero — the checking has stopped, which is worse than errors
  • A sustained 100% acceptance rate for any flag type — triggers review for rubber-stamping (a highly specific emergency rule may legitimately sit at 100%; the trigger is review, not an automatic defect)
  • A rule nobody will own — if no named clinician will put their name to it, it does not enter the register
  • MHRA advice not yet sought, at the stage 2 boundary
Not a mockup

Open the engine
and try to break it

The intake tool is a working rule engine, not a picture of one. Answer the questions and the rules evaluate as you go, each finding naming the rule that raised it, the guideline that rule enforces, the clinician who owns it, and the professional who holds the decision.

Fifty dummy scenarios are loaded — care homes, nursing homes, discharge and end of life, falls, podiatry and diabetes, safeguarding, community concerns, social prescribing, carers and households, acute presentations and advance care planning. All fictional. Load one and watch what fires.

Open the intake tool

Four worth showing a clinical team

  • Scenario 45 — carer admitted, wife has dementia. Two rules fire and a separate record is raised for her. Four lines of logic, no intelligence at all.
  • Scenario 43 — visit for the wife, husband also frail. The household rule and the coverage gap, because he is in nobody's denominator.
  • Scenario 39 — postman raises a concern. No sources available, so almost nothing can fire — and the engine says so rather than guessing.
  • Scenario 09 — annual review, nothing acute. Included deliberately. An engine that fires on everything is useless.

What it is not

Nothing persists — close the tab and it is gone. Nothing is transmitted. It reads no records; every input is typed by hand. This browser demonstration is not deployed for clinical care — but clinical safety engineering begins during development, not at go-live. Before any live use, Skeina will complete the applicable DCB0129 manufacturer clinical-risk-management activities, and each deploying organisation will undertake DCB0160; DTAC, DSPT and a DPIA are additionally required for deployment. NHS England is reviewing DCB0129/0160 during 2026, and Skeina's safety case will track the revised standards.